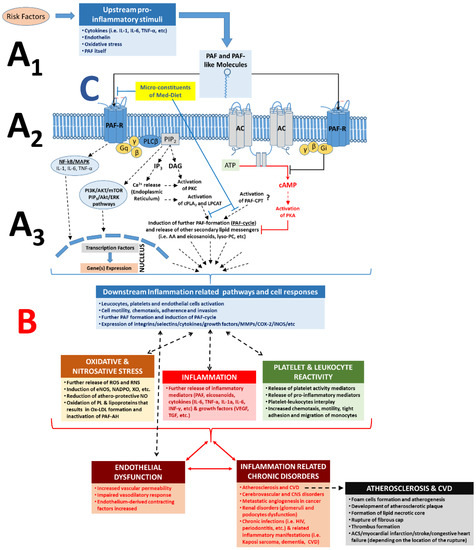
Role of PAF, PAF-R, and its related pathways in the inflammatory cascades and in the pathogenesis of inflammation-related chronic disorders; increased PAF levels by pro-inflammatory stimuli and binding of PAF on its receptor, PAF-R, on the membranes of several cell types can lead to intracellular cascades and a PAF cycle-related amplification of the initial stimuli (A) and in numerous cell responses according to each cell type (B), which can lead to endothelial dysfunction and the onset and progression of inflammation-related chronic diseases. A1. Several risk factors and related upstream pro-inflammatory stimuli trigger formation of PAF and PAF-like molecules (i.e., oxidised phospholipids) and expression of PAF-R. A2. Binding of PAF/PAF-like molecules on PAF-R promote several inflammation-related intracellular pathways; activation of the PAF-R signalling initiates (through a Gq-linked mechanism) PLCβ-mediated hydrolysis of PIP2 to produce IP3 and DAG, leading to transient elevation of cytosolic Ca2+ released from intracellular stores and activation of PKC. The rise in Ca2+ also activates cPLA2α, leading to the release of AA and lysophosphatides, which can serve as substrates for further synthesis of eicosanoids and PAF, respectively. Signalling through Gi-linked PAF-R inhibits the conversion of ATP to cAMP by adenylate cyclase, in this way preventing the activation of PKA and related anti-inflammatory signalling events. A3. Activation of the PAF/PAF-R intracellular pathways leads to the activation of cPLA2 and PAF biosynthetic enzymes (LPCAT) for further formation of PAF and other lipid second messengers, thus creating a PAF cycle and further amplification of the initial inflammatory stimuli, while expression of genes involved in inflammatory manifestations (such as genes of several cytokines, integrins, selectins, metalloproteinase, several enzymes for eicosanoids, and ROS, etc.) is also induced. The pathways inducing the PAF-CPT-related synthesis of PAF are not fully elucidated. B. Increased PAF levels at the site of inflammation and ligand binding (PAF and/or oxidised phospholipids binding) on PAF-R can promote a broad spectrum of PAF effects depending on the cell type and tissue, which is achieved through the production and release of various downstream mediators, such as PAF itself and several other mediators of inflammation such as eicosanoids, cytokines (i.e., TNF-α, IL-1α, IL-6, IL-8, INF-γ, etc.), growth factors (i.e., VEGF, IGF, TGF), ROS, and RNS, but also through the expression of selectins and integrins (i.e., ICAM, VCAM, P-Selectin, E-Selectin) in the membranes of activated cells. Thus, increased downstream mediators, PAF levels, and the subsequent further activation of the PAF/PAF-R pathways promotes the activation and aggregation of platelets and leukocytes, activation of endothelial cells, leukocyte adherence, motility, chemotaxis, invasion, migration, and subsequent endothelial dysfunction, thus stimulating the onset and development of inflammation-related chronic diseases and disorders. C. Microconstituents of several foods of the Mediterranean diet have been found to beneficially inhibit the PAF/PAF-R pathways and PAF synthesis towards homeostatic re-equilibration of PAF levels and activities [57]. PAF: platelet-activating factor; PAF-R: G-protein-coupled PAF-receptor; AC: adenylate cyclase; NF-kB: nuclear factor-kappa light-chain-enhancer of activated B cells; MAPK: mitogen activated protein kinase; ERK: extracellular signal-regulated kinases; Akt: protein kinase B; PI3K: phosphatidylinositol 3-kinase; mTOR: mechanistic target of rapamycin; DAG: diacylglycerol; AA: arachidonic acid; cPLA2: cytosolic phospholipase A2; PKC: protein kinase C; PKA: protein kinase A; LPCAT: acetyl-CoA: lyso-PAF acetyltransferases; PAF-CPT: dithiothreitol l-insensitive CDP-choline: 1-alkyl-2-acetyl-sn-glycerol cholinephosphotransferase; ATP: adenosine triphosphoric acid; cAMP: cyclic adenosine monophosphate; PLC: phospholipase C; MMP: metalloproteinase; COX: cyclooxygenase; iNOS: nitric oxide synthase; eNOS: endothelial nitric oxide synthase; ROS: reactive oxygen species; RNS: reactive nitrogen species; NADPO: nicotinamide-adenine dinucleotide phosphate oxidase; XO: xanthine oxidase; IL-6: interleukin-6; IL-1: interleukin-1; TNFα: tumour necrosis factor-α; ACS: acute coronary syndrome; VEGF: vascular endothelial growth factor; PL: phospholipids; CVD: cardiovascular diseases; CNS: central nervous system.
[ the figure is from our paper: Inflammation, not Cholesterol, Is a Cause of Chronic Disease ]
= = = = = = = = = = = =
Four years ago, the European Heart Journal published a paper titled "Low-density lipoproteins [LDLs] cause atherosclerotic cardiovascular disease: pathophysiological, genetic, and therapeutic insights: a consensus statement from the European Atherosclerosis Society Consensus Panel."
Unfortunately, some researchers have cited this paper as proof that LDLs cause atherosclerosis, just as the title suggests. But if we analyze the content of the paper, we will find that it implicates modified LDLs.
Thus, the true title should read:
Modified low-density lipoproteins cause atherosclerotic cardiovascular disease.
To illustrate why, let us look at examples.
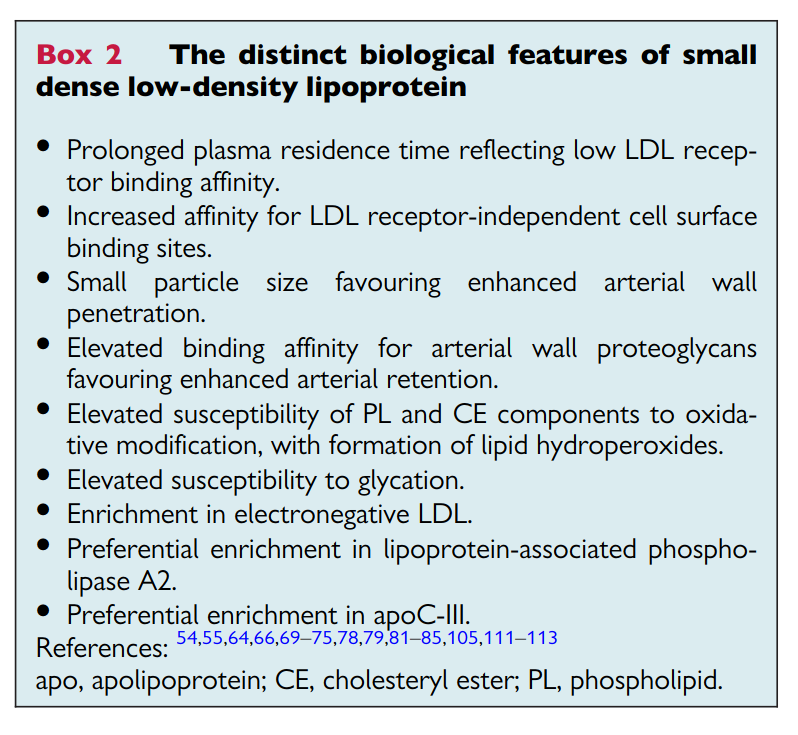
(Image: Taken from the Borén et al.)
And many researchers agree.
Ikezaki and colleagues, for example, have repeatedly stated that small dense LDL is the "most atherogenic lipoprotein parameter" (see here, here, and here).
Deeper in the paper, the European Consensus Panel states:
Several early studies involving quantitative coronary angiography without or with intravascular ultrasound demonstrated modest but significant benefits from statin-mediated LDL lowering on the degree of coronary artery stenosis.
But one of the cited studies showed that changes in LDL size had the strongest association with coronary stenosis, which was considerably stronger than the associations for apoB or LDL cholesterol.
More recently, Jung et al. (2023), McGarrah et al. (2022), Sekimoto et al. (2022), Sæther et al. (2023), Ceponiene et al., (2021), and Aneni et al. (2019) did not find harmful relationships between large LDL particles and atherosclerosis.
Modified and Oxidized LDLs
Besides small dense LDL, the European Consensus Panel mentions the words "modified" and "oxidized" (or related words) throughout the paper.
These modified LDLs, they note, are linked to many aspects of atherosclerosis, including inflammation and thrombosis.
By contrast, the paper mentions "native" or non-modified LDL only a few times. But even in those cases, the data implicated modified LDL.
For example, take the following statement:
Both native and oxidized forms of LDL may prime platelets and increase platelet activation in response to various agonists, thereby contributing to increased risk of atherothrombosis.
But the cited papers (here and here) did not implicate native LDL.
The second paper, for example, explicitly concluded:
L5 but not L1 induced tissue factor and P-selectin expression in human aortic ECs, thereby triggering platelet activation and aggregation with activated ECs. These findings indicate that elevated plasma levels of L5 may promote thrombosis that leads to STEMI [ST-elevation myocardial infarction].
And:
LDL-cholesterol levels were similar between patients with STEMI and control subjects. However, the mean L5% was significantly elevated in STEMI patients compared with that in control subjects.
L5 is a modified LDL called electronegative LDL, which may be a form of oxidized LDL.
Researchers also propose that modified LDLs are more likely to be retained in the arteries. Just last year, for instance, Law and colleagues found that the arteries of animals tend to retain L5 LDL and that L5 LDL (but not L1 LDL) has atherogenic properties.
As they stated:
L1 LDL [the least electronegative LDL] has no negative effects and just provides nutrients; in contrast, L5 [the most electronegative LDL] is highly atherogenic even at low concentrations such as 5 mg/dL.
Vulnerable Plaques
According to the European Consensus Panel:
A pioneering investigation of bilateral, biopsied carotid endarterectomy samples at baseline and after 6 months of pravastatin treatment was seminal in demonstrating statin-induced increases in collagen content and reductions in lipid content, inflammatory cells, metalloprotease activity, and cell death, all of which favour plaque stabilization.
But statin treatment is not the same as LDL treatment.
In two studies the Panel cited, the data showed that statins may have antioxidant and anti-inflammatory effects independent of lipid-lowering effects, and that statins reduce oxidized LDL independent of any effect on LDL-C or total cholesterol.
Why is this important?
Well, unlike normal LDL, oxidized lipoproteins, oxidized lipids, and oxidative stress are associated with plaque vulnerability.
OxLDLs play key roles in the initiation and progression of atherosclerosis and previous studies have shown a strong association between plasma OxLDLs and plaque instability in coronary and carotid artery disease [Kim et al., 2020].
Transcytosis
In the discussion of transcytosis — a process by which LDL is transported across endothelial cells — the European Consensus Panel states:
Many risk factors modulate the propensity of LDL and other atherogenic lipoproteins to traverse the endothelium and enter the arterial intima.
But the cited paper notes:
The first regulator of LDL transendothelial passage is the glycocalyx, a thick and negatively charged matrix layer, that lines the inner wall of healthy blood vessels. . . . It is known that the glycocalyx is severely impaired in diabetes, a disease accompanied by enhanced ROS [reactive oxygen species] production. Furthermore, ox-LDL [but not normal LDL] reduce the effective thickness of the glycocalyx.
Similarly, Lankin, Tikhaze, and Melkumyants (2023) stated:
Numerous studies showed that the leading factor responsible for damage to the glycocalyx and abnormal endothelial performance in atherosclerosis is the oxidative stress.
The European Consensus Panel also ignores the "outside-in" hypothesis, where most lipoproteins enter the coronary intima from the adventitia (the outer layer of the artery) through immature, fragile, and leaky neovessels.
In fact, the Panel cited an autopsy study by Nakashima and colleagues (2007). But according to Subbotin (2016), Haverich and Boyle (2019), and one author of that study, the data were consistent with the outside-in hypothesis:
The fact that the lipid builds up in the outer layer of the intima and not within the intima close to the lumen raises questions as to whether circulating lipid may be coming from the vasa vasorum rather than the luminal side of the vessel [Wight, 2018].
In 2022, Goldberg and Khatib also criticized the transcytosis hypothesis, stating:
By extensively reviewing the existing evidence, we could reasonably conclude that most lipoproteins enter the wall of large arteries not from the lumen by transcytosis but through the vv [vasa vasorum].
Incidentally, oxidized LDL may affect the small blood vessels of the adventitia. Singla et al. (2021), for example, found that oxidized LDL in the adventitia may harm the lymphatic vessels. But they did not observe this harm with native LDL.
Intimal Thickening
Another topic the European Consensus Panel mentioned was intimal thickening:
Autopsy studies in young individuals demonstrated that atherosclerosis-prone arteries develop intimal hyperplasia, a thickening of the intimal layer due to accumulation of smooth muscle cells (SMCs) and proteoglycans. In contrast, atherosclerosis-resistant arteries form minimal to no intimal hyperplasia.
I agree with the Panel that intimal thickening is "critical to the sequence of events leading to plaque formation," and that disturbances in blood flow or hemodynamic stresses cause intimal thickening.
But as with many aspects of atherosclerosis, oxidative stress can contribute. For example, intimal thickening in the prenatal or infancy period is associated with maternal smoking, possibly caused by oxidants in cigarette smoke.
Atherosclerosis Regression
The European Consensus Panel states:
Beyond atherosclerosis progression are questions relating to mechanisms of plaque regression and stabilization induced following marked LDL-cholesterol (LDL-C) reduction by lipid-lowering agents.
The Panel cites five studies here. But two of those studies were about Lp(a), and another study was one I already cited above.
This leaves us with two studies: ASTEROID and SATURN.
In the ASTEROID study, LDL had no association with atherosclerosis regression:
The on-treatment atheroma volume, change in atheroma volume, and high percentage of subjects with atheroma regression did not differ by the achieved LDL cholesterol . . . Atheroma regression occurred in most patients and was not linked to the LDL cholesterol achieved.
The researchers also admitted that statins have pleiotropic effects:
These multiple mechanisms of the beneficial effects of statins could explain why event reduction and lesion modification correlated poorly with LDL cholesterol lowering alone.
Meanwhile, in the SATURN study, there was no convincing evidence of benefit for lower LDL levels:
Despite the lower level of LDL cholesterol and the higher level of HDL cholesterol achieved with rosuvastatin, a similar degree of regression of PAV was observed in the two treatment groups.
Modified LDL, on the other hand, might be a better marker. Tani and colleagues, for instance, found that the change in modified LDL was associated with atherosclerosis regression, but the change in LDL cholesterol was not.
Calcification
On the topic of coronary calcification, the Panel claimed:
Although the role of LDL in coronary artery calcification remains unclear, it is well-established that an elevated LDL-C level is a strong risk factor for progression of calcification.
But the cited study showed a weak correlation (i.e., a correlation coefficient of only 0.25). As such, many individuals with higher LDL levels had similar or less progression of coronary calcification compared to individuals with lower LDL levels.
Furthermore, the Panel noted in the next sentence that modified LDL is likely the problem:
Modified LDL stimulates vascular calcification by driving osteoblastic differentiation of vascular SMCs, while inhibiting osteoclast differentiation of macrophages. In contrast, HDL appears to exert beneficial effects on vascular calcification . . .
Thus, as Allison and Wright stated two decades ago:
The relationship between LDL cholesterol and atheroma development is dependent on the oxidized form of LDL. Biochemical research has provided evidence that low-density lipoprotein cholesterol can promote atherosclerotic calcification of vascular cells. However, this effect was found to be due to products of lipid oxidation and not a function of native LDL or its concentration in serum.
A Chat with Dr. Borén
Interestingly enough, I had a short email exchange with the lead author of the consensus paper, Jan Borén, six months before the paper was published.
Before the consensus paper, Borén and Williams (2016) published a paper claiming that oxidized LDL was a mere "bystander" in cardiovascular disease. But I was unconvinced.
Therefore, in 2019, I emailed Dr. Borén and challenged his paper with contrary evidence. After a few back-and-forth emails, he agreed that many things about atherosclerosis are still unclear and we should remain open-minded.
What I could not predict, however, was that six months after this email exchange, Borén and colleagues would feature oxidative stress as a major part of their argument!
Oxidative stress even appears in their take-home figure:
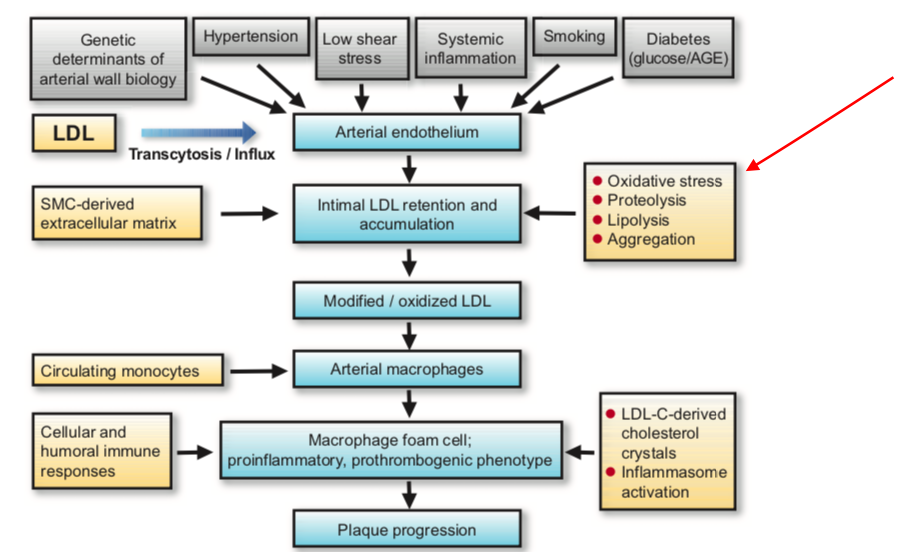
But since oxidative stress (OS) is related to the risk factors in grey (top of the figure), a more accurate diagram would be the one from Bale and colleagues (2022):
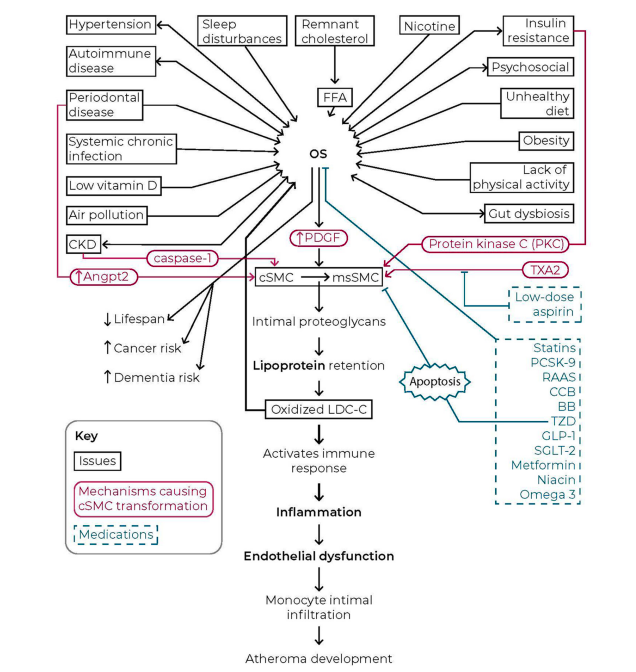
This diagram is not perfect as well, but it's a start.
For example, these diagrams assume that LDLs become modified only after getting "stuck" in the artery. But modified LDLs in blood circulation could also be caused by other factors, such as oxidized lipids in the diet (Ahotupa et al., 2009; Addis and Grootveld, 2021; Spiteller, 2007; Gonçalinho et al., 2023).
Conclusions
Contrary to what supporters of the lipid hypothesis claim, the European Consensus Panel did not prove that LDL itself is harmful. Instead, the Panel made the case that modified LDLs drive the disease.
Therefore, as Sánchez-Quesada and colleagues wrote:
Native LDL does not present any of the typical features of an atherogenic lipoprotein. It is not inflammatory, apoptotic or recognized by scavenger receptors. Furthermore, its binding to arterial proteoglycans is low. Therefore, there is a general consensus that LDL must be modified in order to acquire atherogenic characteristics [bold emphasis mine].
= = = = = = = = = = = = = =
the full paper is here.

